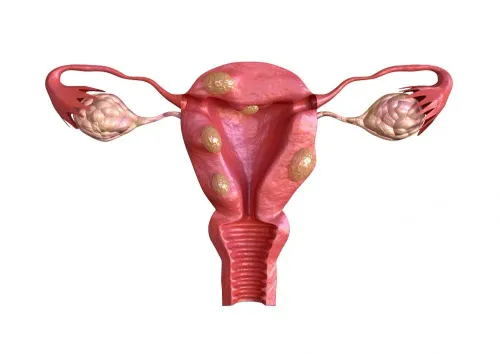
Irregular periods, sudden acne, facial hair, hair loss, weight change or hot flashes can have several causes, and a random “hormone panel” rarely explains them. By the end, you will know what a doctor evaluates, how to prepare, which tests may be timed to your cycle, and how treatment differs between conditions.
Key takeaways
- Bring your symptom timeline, menstrual dates, medicines and previous test reports.
- Ask which hormone test timing matches your cycle and suspected condition.
- Treat the underlying cause rather than relying on a generic hormone medicine.
- Plan follow-up around symptom changes, test results and treatment safety checks.
What a hormonal imbalance doctor checks at your first appointment
A hormonal imbalance doctor in Thane first clarifies the problem before ordering tests. “Hormonal imbalance” is not a diagnosis. The clinician records when the main symptom began, whether it is changing, and whether it follows a cycle pattern, then checks weight, blood pressure, thyroid, skin, hair and abdomen or pelvis when indicated.
1. They ask for menstrual dates, cycle length, skipped periods, bleeding volume, clots, pain and spotting. They also ask about acne, new facial or body hair, scalp hair loss, nipple discharge, weight change, sleep, stress and hot flashes.
2. They review current medicines, steroids, psychiatric medicines, thyroid medicines, contraception and supplements, along with any recent pregnancy. Do not omit non-prescription products.
3. They ask about pregnancy plans and past ovarian or thyroid problems, diabetes, migraine, blood clots, breast disease and family history.
4. If periods are late, pregnancy must be considered first, even when another cause seems likely.
An occasional late cycle after illness or major stress can be normal.
Book an assessment for repeated cycles shorter than 21 days or longer than 35 days, bleeding over 7 days, soaking a pad or tampon hourly for several hours, three months without a period when not pregnant, new virilising symptoms, persistent milk discharge or troublesome hot flashes.
How to prepare and choose the right women’s health specialist
Bring a six-cycle record, relevant reports and a complete medicine list to make the appointment useful. Record the first day of each of your last six menstrual periods, cycle length, bleeding days, pad or tampon use, pain, spotting and home pregnancy-test results.
- Bring prior ultrasound and blood reports, discharge summaries, and vaccination or pregnancy records when relevant.
- Write every medicine’s name, dose and start date, including contraception, supplements and steroids.
- Add a symptom timeline covering changes in weight, acne, facial or body hair growth or loss, scalp hair loss, sleep, mood and nipple discharge.
A gynaecologist is the practical first clinician for irregular or heavy bleeding, ovulation concerns, contraception, pelvic symptoms and hormone symptoms linked to reproductive stages. A hormone specialist gynaecologist in Thane should coordinate referrals rather than assume every symptom is ovarian.
| Specialist | Best first choice when |
|---|---|
| Gynaecologist | Bleeding, ovulation, contraception, pelvic symptoms or reproductive-stage hormone symptoms |
| Endocrinologist | Confirmed thyroid, diabetes, adrenal or pituitary disease, or difficult prolactin abnormalities |
| Dermatologist | Acne or hair loss dominates after medical causes are assessed |
| Fertility specialist | Pregnancy has not occurred or ovulation induction is needed |
| Primary-care doctor | You need basic testing or management of a general condition |
Choosing the wrong starting point can delay a pregnancy test, bleeding assessment or treatment for a non-ovarian condition.
Which tests matter, and why timing changes the result
A random female hormone panel is unreliable because reproductive hormones change with cycle day, age, pregnancy, contraception, medicines and assay method. A women hormone doctor in Thane should order each test to answer a defined question, not use a broad panel as screening.
Pregnancy comes first: use a urine or blood test when pregnancy is possible. Serum TSH usually starts thyroid assessment; add free T4 when TSH is abnormal or central thyroid disease is suspected. Check prolactin for persistent milk discharge or cycle disruption. If mildly raised, repeat it after avoiding strenuous exercise and breast stimulation.
| Clinical question | Tests or assessment | Timing or limitation |
|---|---|---|
| Androgen symptoms | Total or free testosterone and DHEAS | Interpret with medicines, contraception and assay method |
| Ovulation or ovarian function | FSH, LH, estradiol; progesterone | FSH, LH and estradiol depend on the condition and cycle stage; time progesterone to the expected luteal phase |
| Metabolic risk | HbA1c, fasting glucose and lipid profile | Assesses associated metabolic risk |
| Pelvic causes | Pelvic ultrasound | Assesses uterus, ovaries and endometrium |
PCOS requires at least two of clinical or biochemical hyperandrogenism, ovulatory dysfunction and polycystic ovarian morphology, after other causes are excluded. Follicles alone do not prove PCOS. AMH measures ovarian reserve and stimulation response, not egg quality or guaranteed natural fertility.
How treatment changes with the actual cause
Personalised hormonal treatment in Thane starts with the confirmed cause, not a generic promise to “balance” hormones. Your fertility plans, age, symptoms, medical risks and test results determine the treatment.
- For PCOS without an immediate pregnancy goal, cycle tracking, movement, nutrition, sleep support and weight-focused care may accompany a combined oral contraceptive for irregular periods, acne or excess hair. Metformin is mainly for metabolic indications and may help some patients with irregular periods; it is not a substitute for contraception.
- For anovulatory PCOS with a pregnancy goal, letrozole is first-line ovulation induction when no other infertility factor changes the plan. It requires medical supervision and pregnancy-focused follow-up.
- Confirmed thyroid disease needs thyroid replacement or another condition-specific treatment. The correct dose depends on thyroid results, symptoms, pregnancy status and other medicines.
- Persistent hyperprolactinaemia may need a prolactin-lowering medicine. Before prescribing, review medicines, pregnancy, macroprolactin and repeat-test conditions, including strenuous exercise or breast stimulation.
- Suspected premature ovarian insufficiency needs disordered cycles for at least four months and elevated FSH on two blood samples taken 4–6 weeks apart. Care may include hormone replacement, bone and cardiovascular risk review, and fertility counselling.
- Perimenopause treatment depends on bleeding pattern and symptoms. Menopausal hormone therapy can relieve troublesome hot flushes or genitourinary symptoms, but systemic oestrogen requires endometrial protection with a progestogen if you have a uterus. Review contraindications, choose regulated products over compounded “bioidentical” preparations, and match treatment to your goals.
How to select a clinic and plan safe follow-up
A good hormonal imbalance doctor in Thane will give you a working diagnosis, not just a prescription. The clinician should link symptoms with cycle timing, medicines and test results, then explain what happens next.
- Name the leading diagnosis and the alternatives being excluded.
- Explain why each test is needed, record your cycle day and list every medicine, contraceptive and supplement.
- Set a review date before treatment starts.
- Define one outcome to monitor: cycle interval, bleeding volume, acne, hair growth, glucose, thyroid levels, prolactin or symptom control.
- Avoid a plan based only on repeating a broad hormone panel.
Follow-up matters after starting contraception, cyclic progesterone, metformin, thyroid treatment, prolactin-lowering therapy, fertility medicines or menopausal hormone therapy.
| Treatment or review target | What to track | Why it matters |
|---|---|---|
| Irregular cycles | Days between periods and bleeding volume | Shows whether cycle control is improving |
| Metformin | Glucose, gastrointestinal effects and cycle pattern | Separates metabolic benefit from side effects |
| Thyroid or prolactin therapy | TSH, free T4 or prolactin when indicated | Confirms dose response |
| Menopausal treatment | Hot flashes, sleep, bleeding and vaginal symptoms | Tests benefit and detects problems |
Seek prompt reassessment for persistent milk discharge, severe headache, visual change, rapidly progressive facial hair, voice deepening, very heavy bleeding, pregnancy-related symptoms or bleeding after menopause. Systemic menopausal hormone therapy needs specialist assessment with unexplained vaginal bleeding, current or previous breast cancer, active liver disease, previous venous thromboembolism or significant cardiovascular disease.
Dr. Chandavakar’s Apeksha Maternity & Nursing Home is one option for coordinated gynaecological evaluation in Thane when menstrual, reproductive, fertility or menopausal concerns overlap. Good hormonal treatment in Thane connects diagnosis, treatment choice and review.
Related service
Hormonal Imbalance Treatment Dr. Madhura Chandavarkar at Apeksha Maternity and Nursing Home provides compassionate and personalized care for women experiencing hormonal... View service → |
Frequently asked questions
What does a hormonal imbalance doctor check at the first appointment?
The doctor records when symptoms began, how they are changing and whether they follow a cycle pattern. The assessment can include weight, blood pressure, thyroid, skin, hair, abdomen and pelvis.
How should you prepare for a hormone consultation?
Take your menstrual dates, symptom timeline, current medicines and supplements, contraception details, pregnancy history and previous reports. Write down your main concerns and questions before the appointment.
Why does timing affect hormone test results?
Hormone levels change during the menstrual cycle and across the day. The correct timing depends on the suspected condition and the test, so follow the clinician’s instructions rather than ordering a panel without guidance.
How does treatment change with the cause of the hormonal problem?
Treatment depends on the finding. Options can include treating thyroid disease, managing polycystic ovary syndrome, addressing high prolactin, supporting fertility, regulating bleeding or reviewing medicines and lifestyle factors.
How do you choose a clinic and plan safe follow-up?
Choose a women’s health specialist who explains the suspected cause, test timing, treatment purpose, side effects and review date. Keep a record of symptoms, bleeding patterns, medicines and follow-up results.
Keywords